Can you work with shingles? Rash coverage and workplace risk
Whether to work with shingles depends on the rash, your health and the people you may contact. A covered localized rash is different from exposed or widespread lesions. Healthcare workers need occupational-health guidance rather than a general office rule.

Transmission is a chickenpox risk for susceptible contacts
Someone who has never had chickenpox and has not been vaccinated against it can develop chickenpox after exposure to varicella-zoster virus from shingles. They do not directly catch shingles. Blister fluid is important, and infectious particles can also be involved, especially with widespread disease.
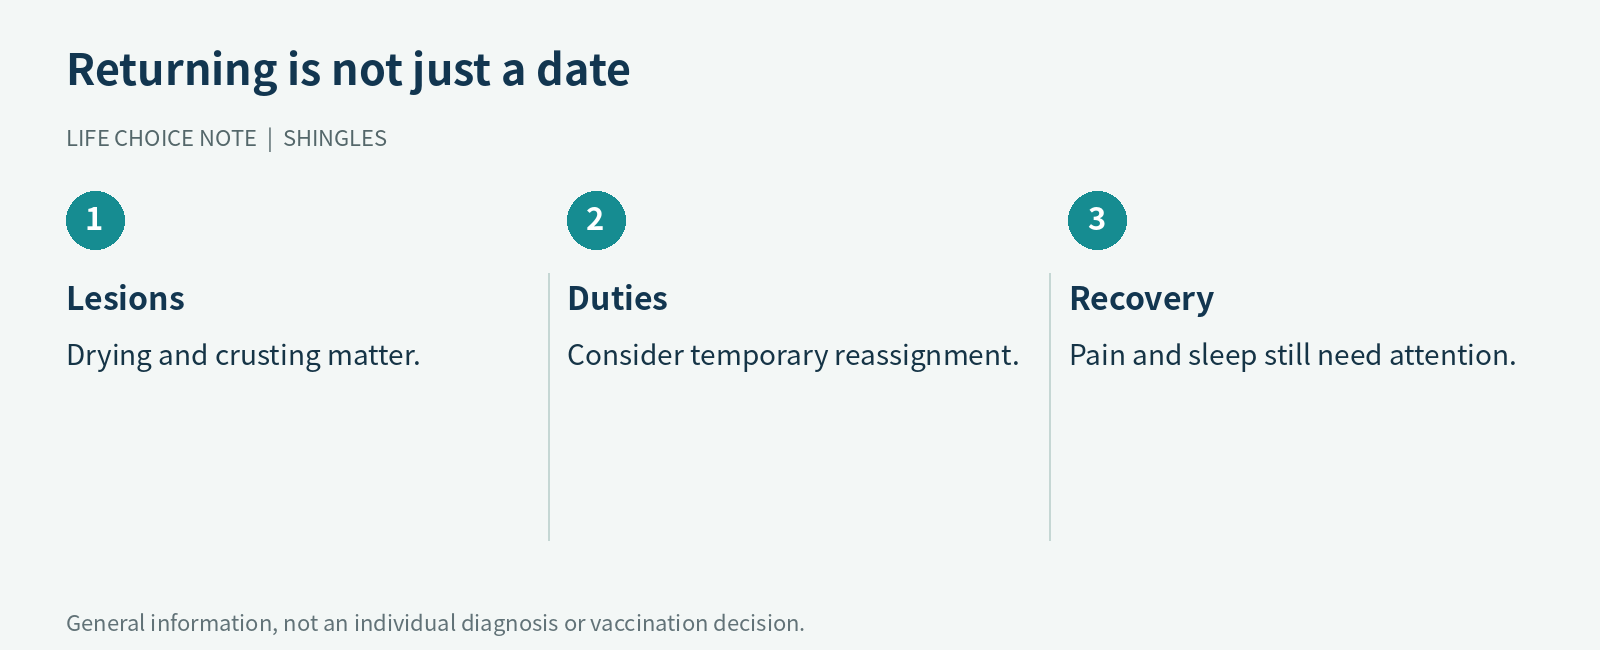
The period of concern generally lasts until lesions have dried and crusted. Keep a localized rash covered when possible and wash your hands. People without immunity who are pregnant, immunocompromised, or newborns need particular protection.

Tap the diagram to view full size
Check the rash before deciding about the workplace
Ask whether lesions are localized or widespread and whether every lesion can remain securely covered. A bandage that repeatedly slips or leaks during work is not reliable coverage. Pain, fatigue and medicine-related drowsiness also affect whether you can work safely.
The NHS advises staying away from work or school when a weeping rash cannot be covered, until it has dried. This is practical public guidance, not a replacement for a workplace-specific policy or a clinician assessing your condition.
Healthcare work has specific restrictions
CDC guidance distinguishes immunocompetent healthcare personnel with localized shingles and coverable lesions from personnel with disseminated disease or immunocompromise. Even with covered localized lesions, avoiding care of patients at high risk may be required where feasible until lesions crust.
CDC recommends excluding healthcare personnel with disseminated shingles, or immunocompromised personnel with localized shingles until dissemination is ruled out, from work until all lesions have dried and crusted. For immunocompetent personnel with localized lesions, or immunocompromised personnel after dissemination has been ruled out, all lesions should be covered and care of high-risk patients avoided when feasible until crusting. If localized lesions cannot be covered, CDC recommends exclusion until they dry and crust. Occupational health should apply this guidance to the actual job.
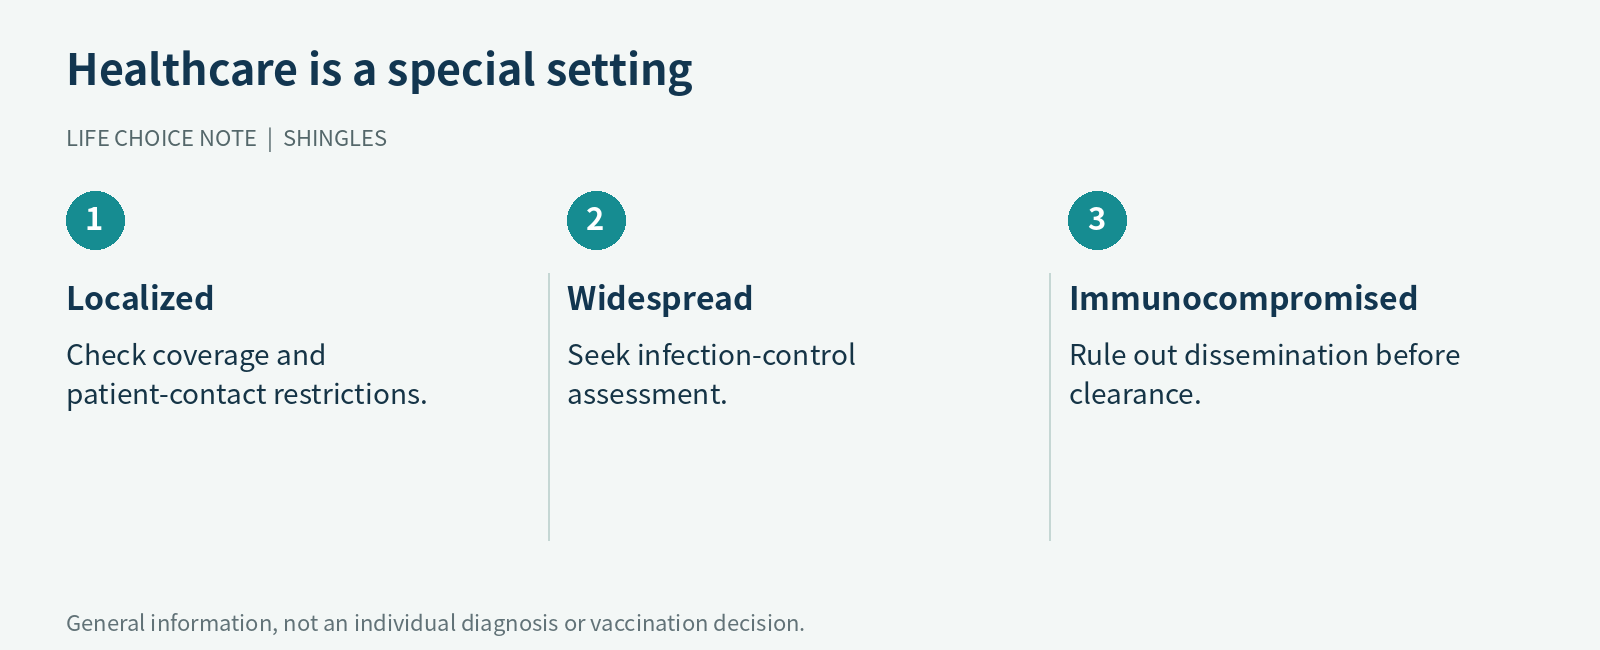
Tap the diagram to view full size
Tell the right person only the information needed
Contact occupational health or your designated workplace manager about rash coverage, duties and vulnerable contacts. Ask whether temporary reassignment or time away is needed. Avoid sending photographs or medical details to a broad workplace chat.
Food handling, childcare and close-contact duties can have additional local requirements. A medical note and the employer’s policy may be needed. The same return-to-work date is not appropriate for every job or every rash.
Treatment does not immediately remove transmission risk
Taking an antiviral or feeling less pain does not automatically mean the lesions are no longer infectious. The condition of the lesions and clinical advice remain relevant. Do not use the number of tablets taken as a clearance test.
If an unprotected contact may have occurred, report it promptly through the appropriate channel. A pregnant or immunocompromised person who may lack varicella immunity should seek medical advice promptly rather than wait for symptoms.
Tap the diagram to view full size
Review attendance and recovery separately
A person may meet an infection-control requirement but still be unable to work safely because of pain, poor sleep or treatment effects. Discuss driving, machinery and demanding duties with the treating clinician.
Reassess if the rash spreads, new lesions appear, or eye, ear or neurologic symptoms develop. Returning to work is one decision; monitoring complications and controlling symptoms remain separate parts of recovery.
Use a clinician’s advice and your workplace’s infection-control rules to decide when and how to return. This article does not certify fitness for work or override local occupational-health requirements.
Sources and review date
- NHS Shingles
- CDC: Varicella-Zoster Virus, Infection Control in Healthcare Personnel
- British Association of Dermatologists: Shingles (Herpes Zoster)
- NHS: Aciclovir
Sources checked October 6, 2026. General health information; discuss individual diagnosis, treatment and vaccination with a qualified healthcare professional.




